tend
One calm screen for a hospital ward.
 Live · opens full screen

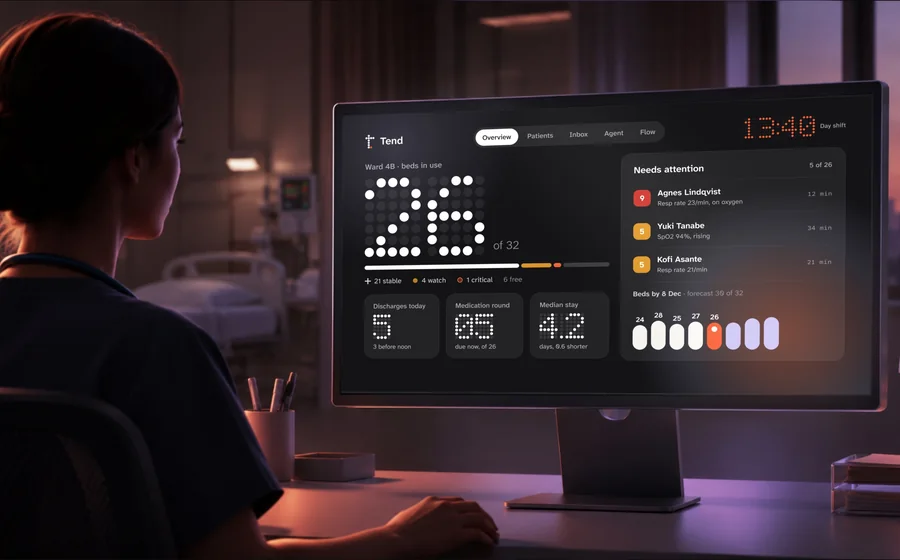
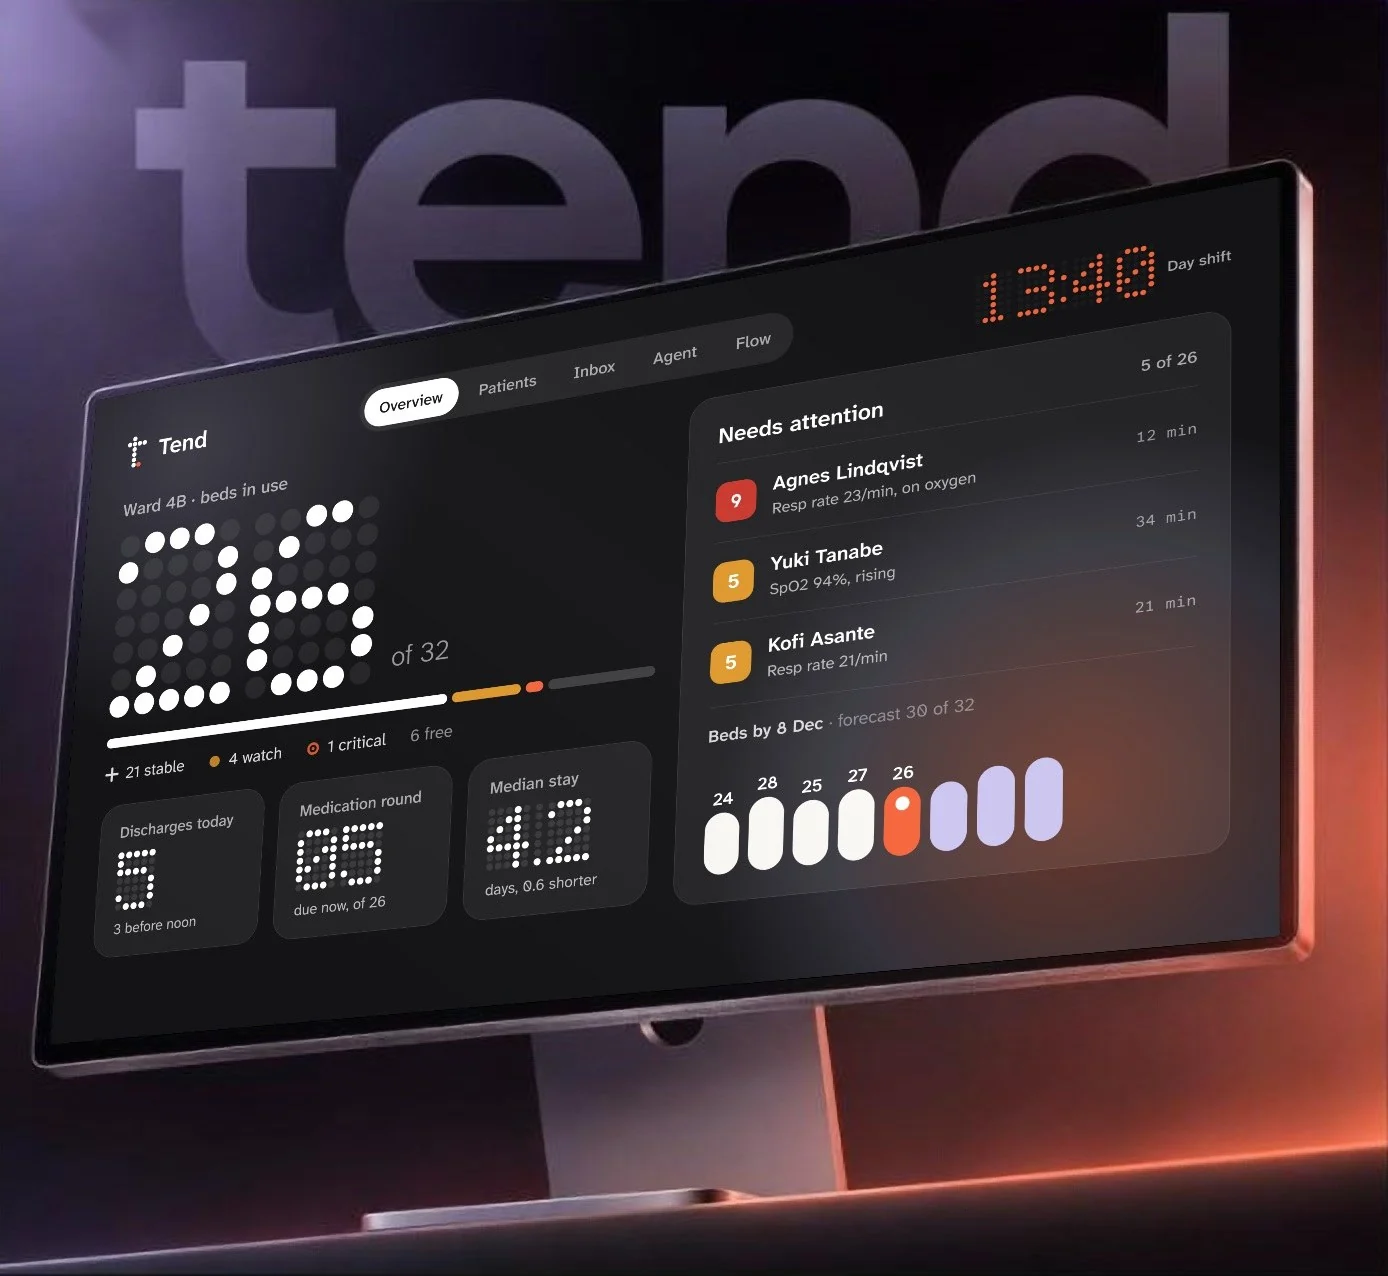
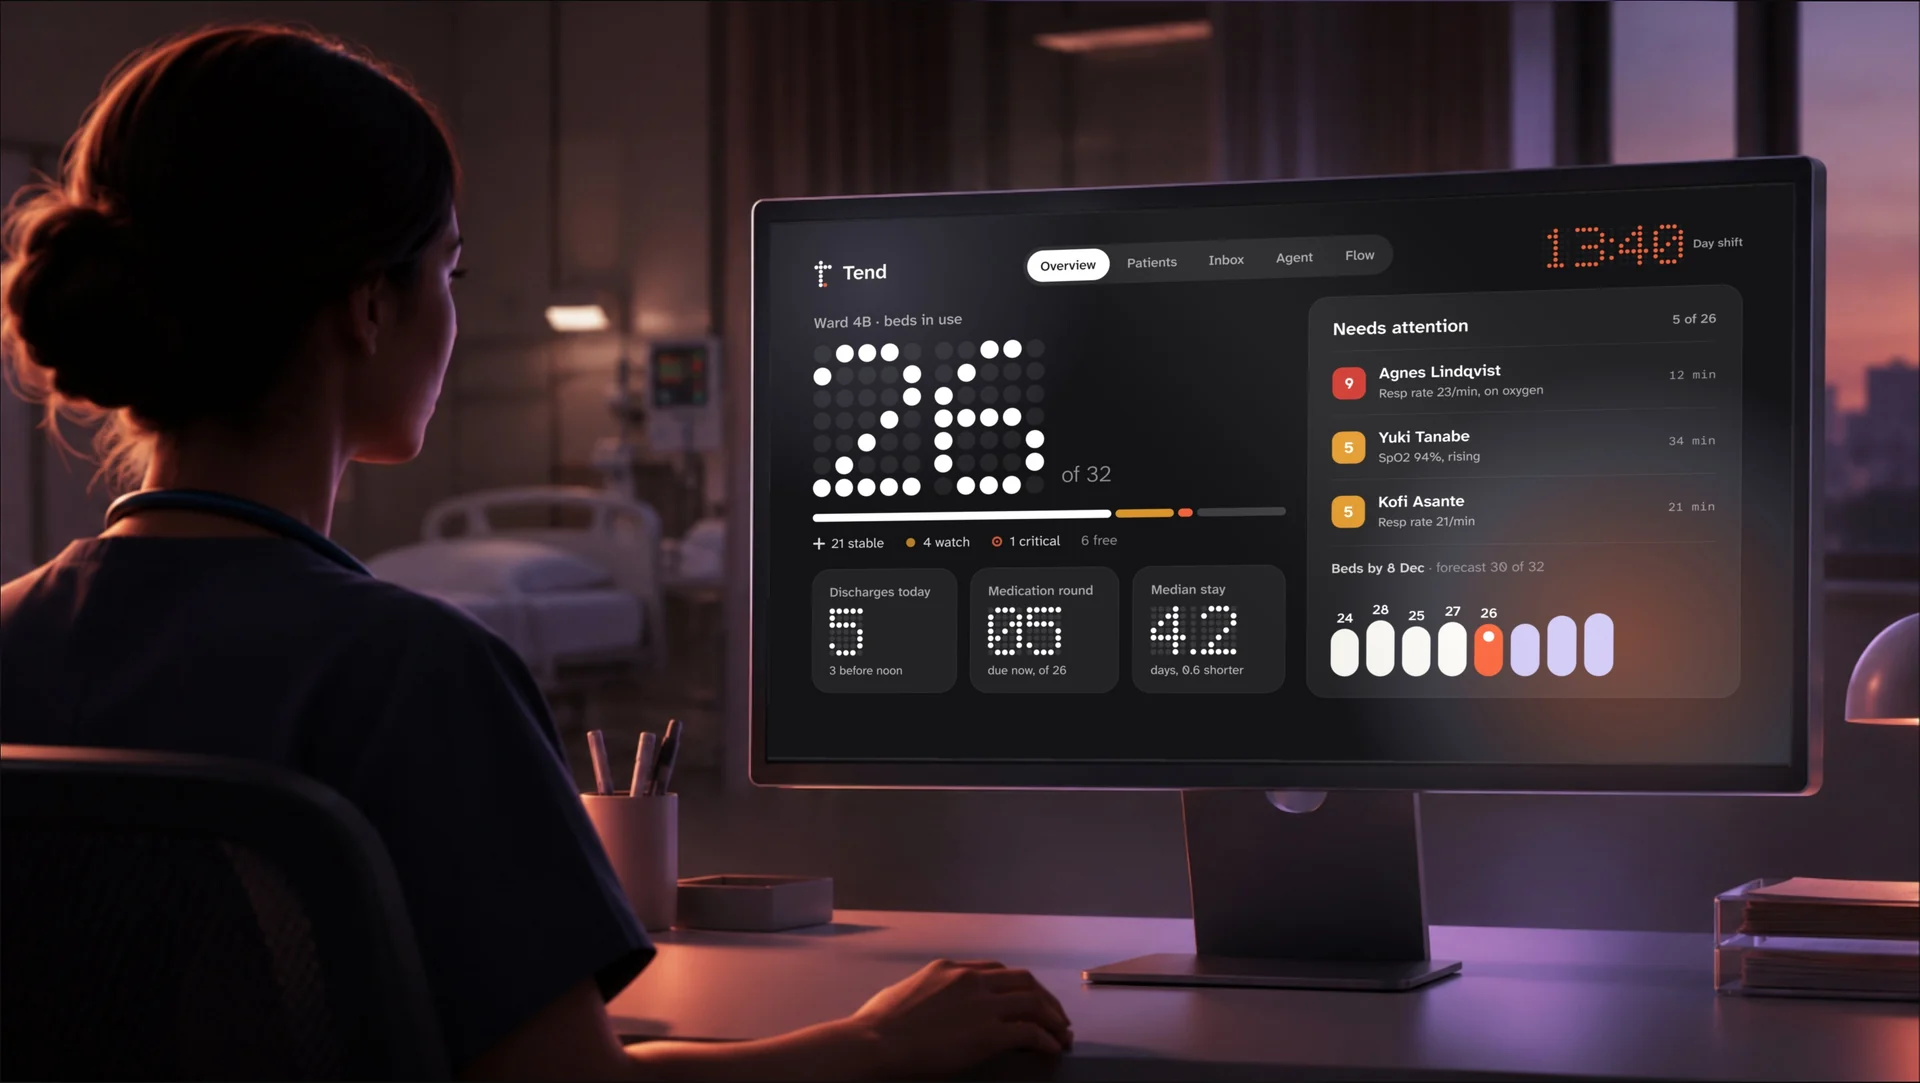 THE WARD OVERVIEW, AT 13:40
Tend is a ward dashboard that tells each person what to do next, shows the reason, and never acts without a human.
A hospital ward runs on small decisions made all day by a handful of people: who to see first, who can go home, which message to answer, which bill is about to be rejected. The information for those decisions lives in six or seven different systems.
Tend puts it on one screen. It is a concept, built as a working prototype with made-up patients, so every screen in this case study is something you can click. I used it to practise a hard design problem: how to put an AI agent in a clinical room without anyone trusting it more than they should.
Too many screens. Too little time.
The numbers below are from published studies and reports. They come from different countries and hospital types, so read them as the size of the problem, not as a promise about any one ward.
flowsheet entries a nurse makes in a 12-hour shift. The study counted 631 to 875. That is about one a minute, all shift.
NYU Langone study, via Tandem Healthto 40 percent of a nursing shift goes on documentation, across studies. One medical-surgical study put it above 41 percent.
Tandem Health review · Schenk et al. 2017, via Medtronichospital beds a day in England hold a patient who is fit to leave. That is close to one bed in ten, in 2025/26.
The King’s Fund, July 2026pounds is the average cost of one hospital bed day. Delayed discharges cost the NHS about £2.7 billion in a year.
The King’s Fund, July 2026The sickest patient is not obviousEarly-warning scores sit inside charts. A rising trend is easy to miss between rounds.
Messages arrive on five channelsPagers, phones, email, the desk, hallway chats. Replies are written from scratch every time.
AI that acts silently is not trustedA black box that changes orders is a safety risk. A black box that only advises, with no reason, gets ignored.
Alert rules live in IT ticketsClinical leads cannot tune an alert and see its cost. Too many alerts cause alarm fatigue.
Discharges stall on one missing tickTransport, pharmacy or a call to family. The blocker is rarely visible where the team looks.
Billing is invisible to the wardClaims are rejected weeks later for something that was fixable while the patient was still here.
Brain scans live in another toolNew MS and Alzheimer’s guidance asks for finer reading, but the viewer is far from the chart.
Small type, look-alike lettersPatient IDs, doses and drug names are read quickly and tired. A misread character is an error.
How might we give a ward one calm screen that shows each person what to do next, explains why, and never acts without a human?
Four people. Four jobs.
These are composite roles drawn from the studies above, not interview subjects. Each one shaped a tab.
Imani, charge nurse
Needs the order to work in, and to know the moment a score climbs.
Dr Menon, consultant
Needs the chart, the scan and the open decisions in one place.
Ben, ward pharmacist
Needs queries to reach the right person and be answered in writing.
Nadia, billing lead
Needs to catch a claim that will fail before it is sent.
Six rules I did not break.
I studied before I redesigned.
Version one of Tend was a clean dashboard. Before version two I studied three published case studies in health and finance tech, and took ideas from each. I list what I kept and what I left out.
MediNexus
Hospital operations dashboard- Heatmap of busy hours, with hatched cells for periods without data
- A clear case-study order: problem, palette, type, cards, devices
- Tooltips that explain a bar in plain numbers
Vital (SpaTheory)
AI-native clinic operations- Problem as a numbered list of eight pains
- “Sense, reason, act” as the model for the AI
- An inbox and a visual automation canvas
- One record per patient and access control
Keel
Cash forecasting, a fintech- One large number, then the reasoning behind it
- A confidence score on every prediction
- Plain-language explanations that can be audited
- Soft shadows and tactile device mockups
Sense. Reason. Act.
Tend reads the chart, ranks what matters, and does the errands. A person decides everything clinical.
Vitals, bloods, drug charts, bed status, messages and claims. Hundreds of readings arrive in a shift, and it reads all of them.
A real NEWS2 score, trends, interactions and blockers, sorted by how soon someone could be hurt.
Chases results, books transport, drafts replies. Anything clinical becomes a card that waits for sign-off.
Eight screens in one tab bar. Keys 1 to 8 jump between them and ⌘K searches patients and actions.
Each screen, in plain words.
For every screen: the problem it solves, what you see, and how it helps. All of them are clickable in the prototype.
Overview
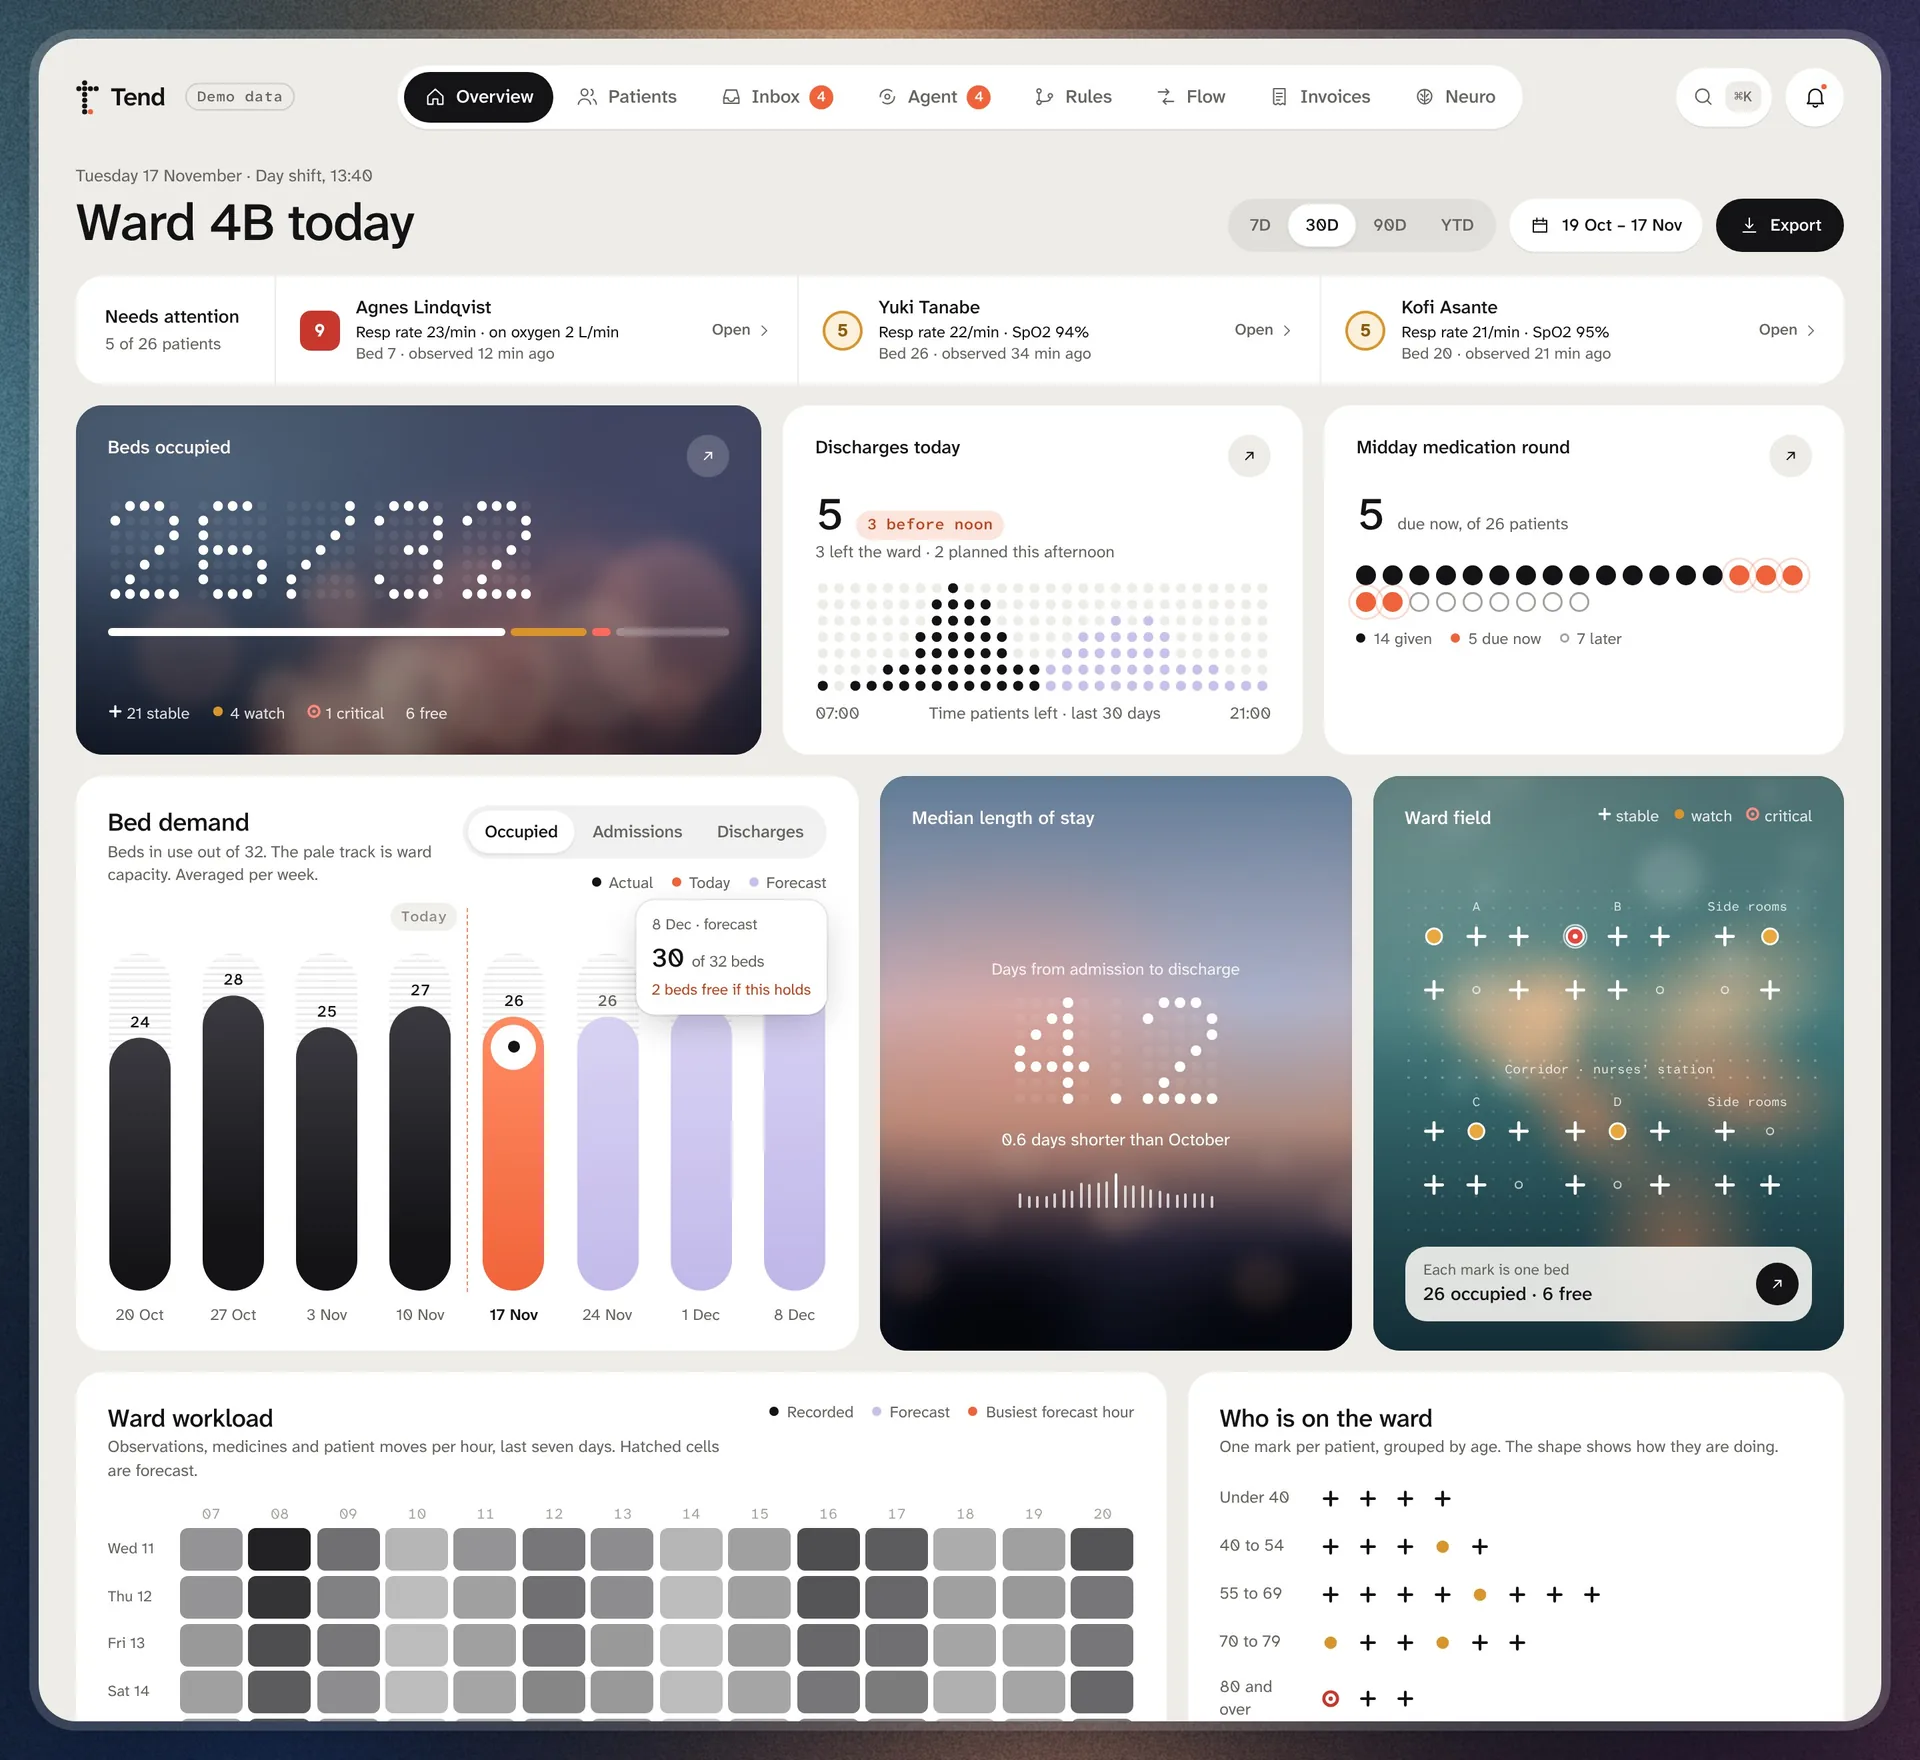
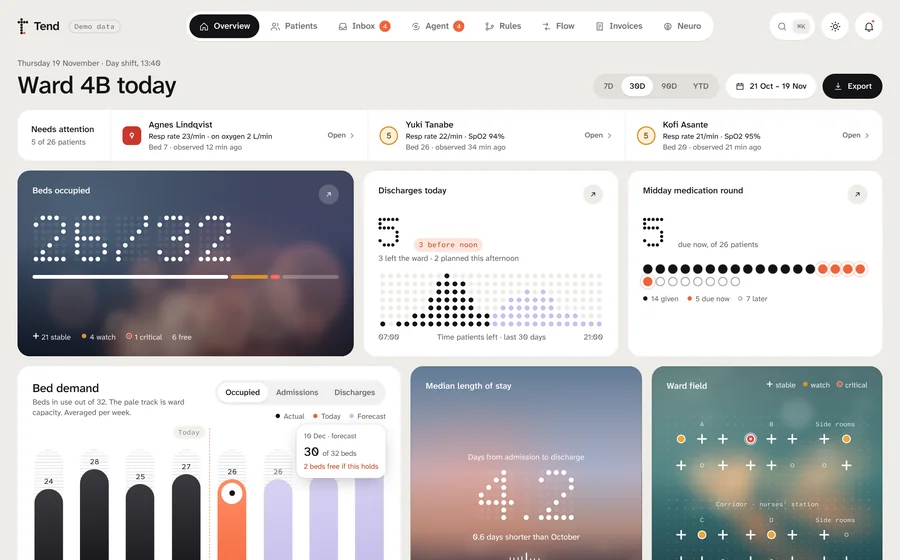
At the start of a shift nobody knows what to look at first. The answers are spread across six screens.
- Needs attention. The three patients most at risk, ranked, with the reason in plain words.
- Beds, discharges, medicine round. Drawn as dots, so counts are exact.
- Bed demand. Capsules for the past, today and the forecast.
- Workload heatmap. Which hours are busy, with the rest of today as a hatched forecast.
- Ward field. One mark per bed. Click one to open the patient.
One glance gives the order to work in. The reason sits beside every score, so no one opens a chart just to find out why a number is high. The heatmap shows when the ward will be busiest, which is a staffing question.
Try: Switch 7D, 30D, 90D or YTD. Hover a capsule or a heatmap cell.
Patients
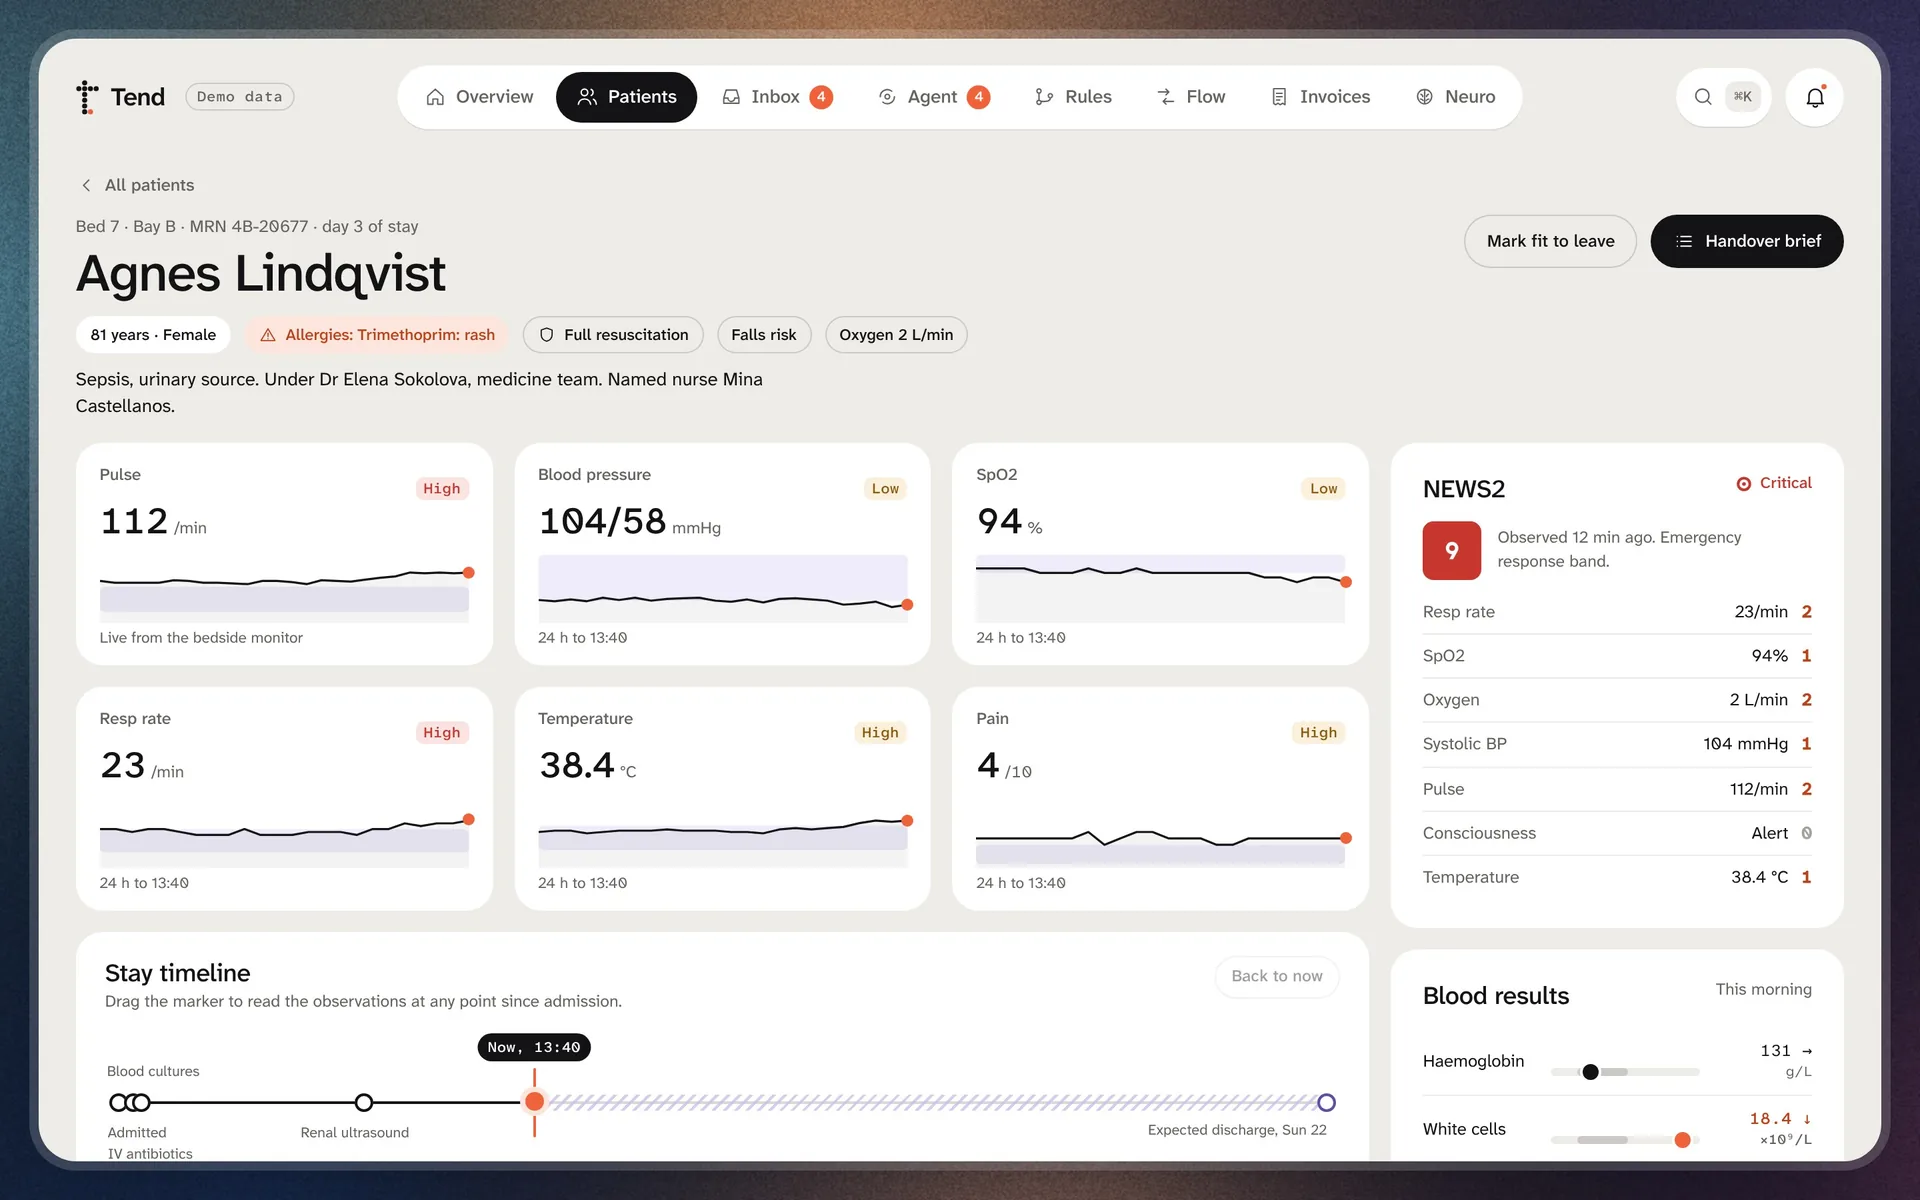
The chart is a long set of tabs. The one question that matters, “is this person getting worse?”, is buried.
- List. Filter, search and sort. Each row carries a small NEWS2 trend.
- Six vitals. A normal band is drawn behind each one, so “high” and “low” are visible.
- NEWS2 breakdown. Each parameter and the points it adds.
- Stay timeline. Drag the marker to read the observations at any hour.
- Medicines, bloods, imaging, team. A button to mark someone fit to leave, and one for the handover brief.
Normal ranges are drawn, not described, so a glance tells you what is off. Scrubbing the timeline shows how the patient looked at any hour, which is what a doctor on a ward round asks.
Try: Open any row. Drag the timeline marker. Press Handover brief.
Inbox
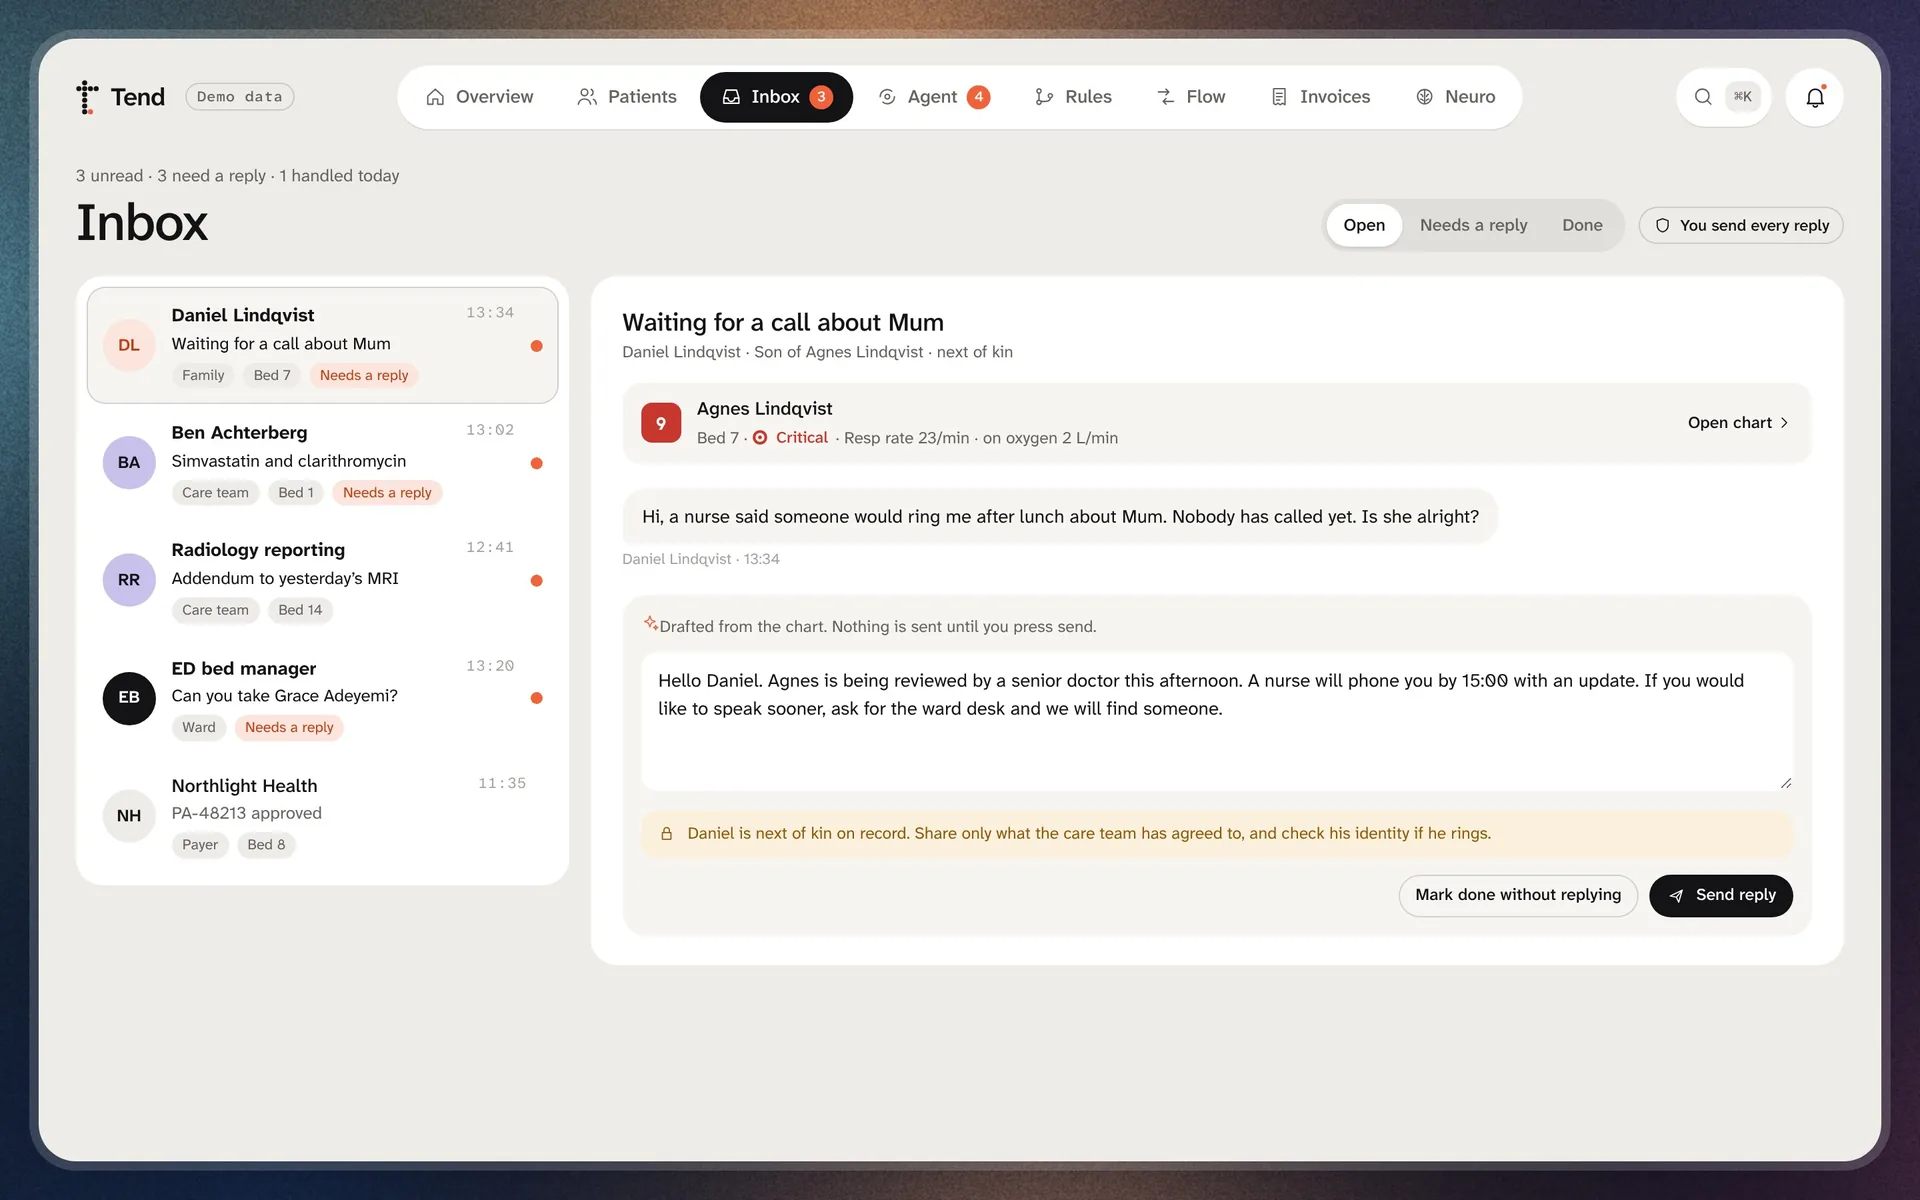
Family calls, pharmacy queries, ED requests and payer replies arrive on phones, pagers and email. Each reply is written from nothing.
- One list. Family, care team, ward and payer, with “needs a reply” marked.
- Chart context. The patient’s score and state sit above the message.
- A drafted reply. Written from the chart. You can edit it.
- A privacy flag. “Check identity. Share only what the team has agreed.”
You answer with the facts in front of you. The agent drafts but never sends, so the person who replies is the person responsible. Messages that need no reply can be cleared in one tap.
Try: Press Send reply, then Undo. Try the “Needs a reply” filter.
Agent
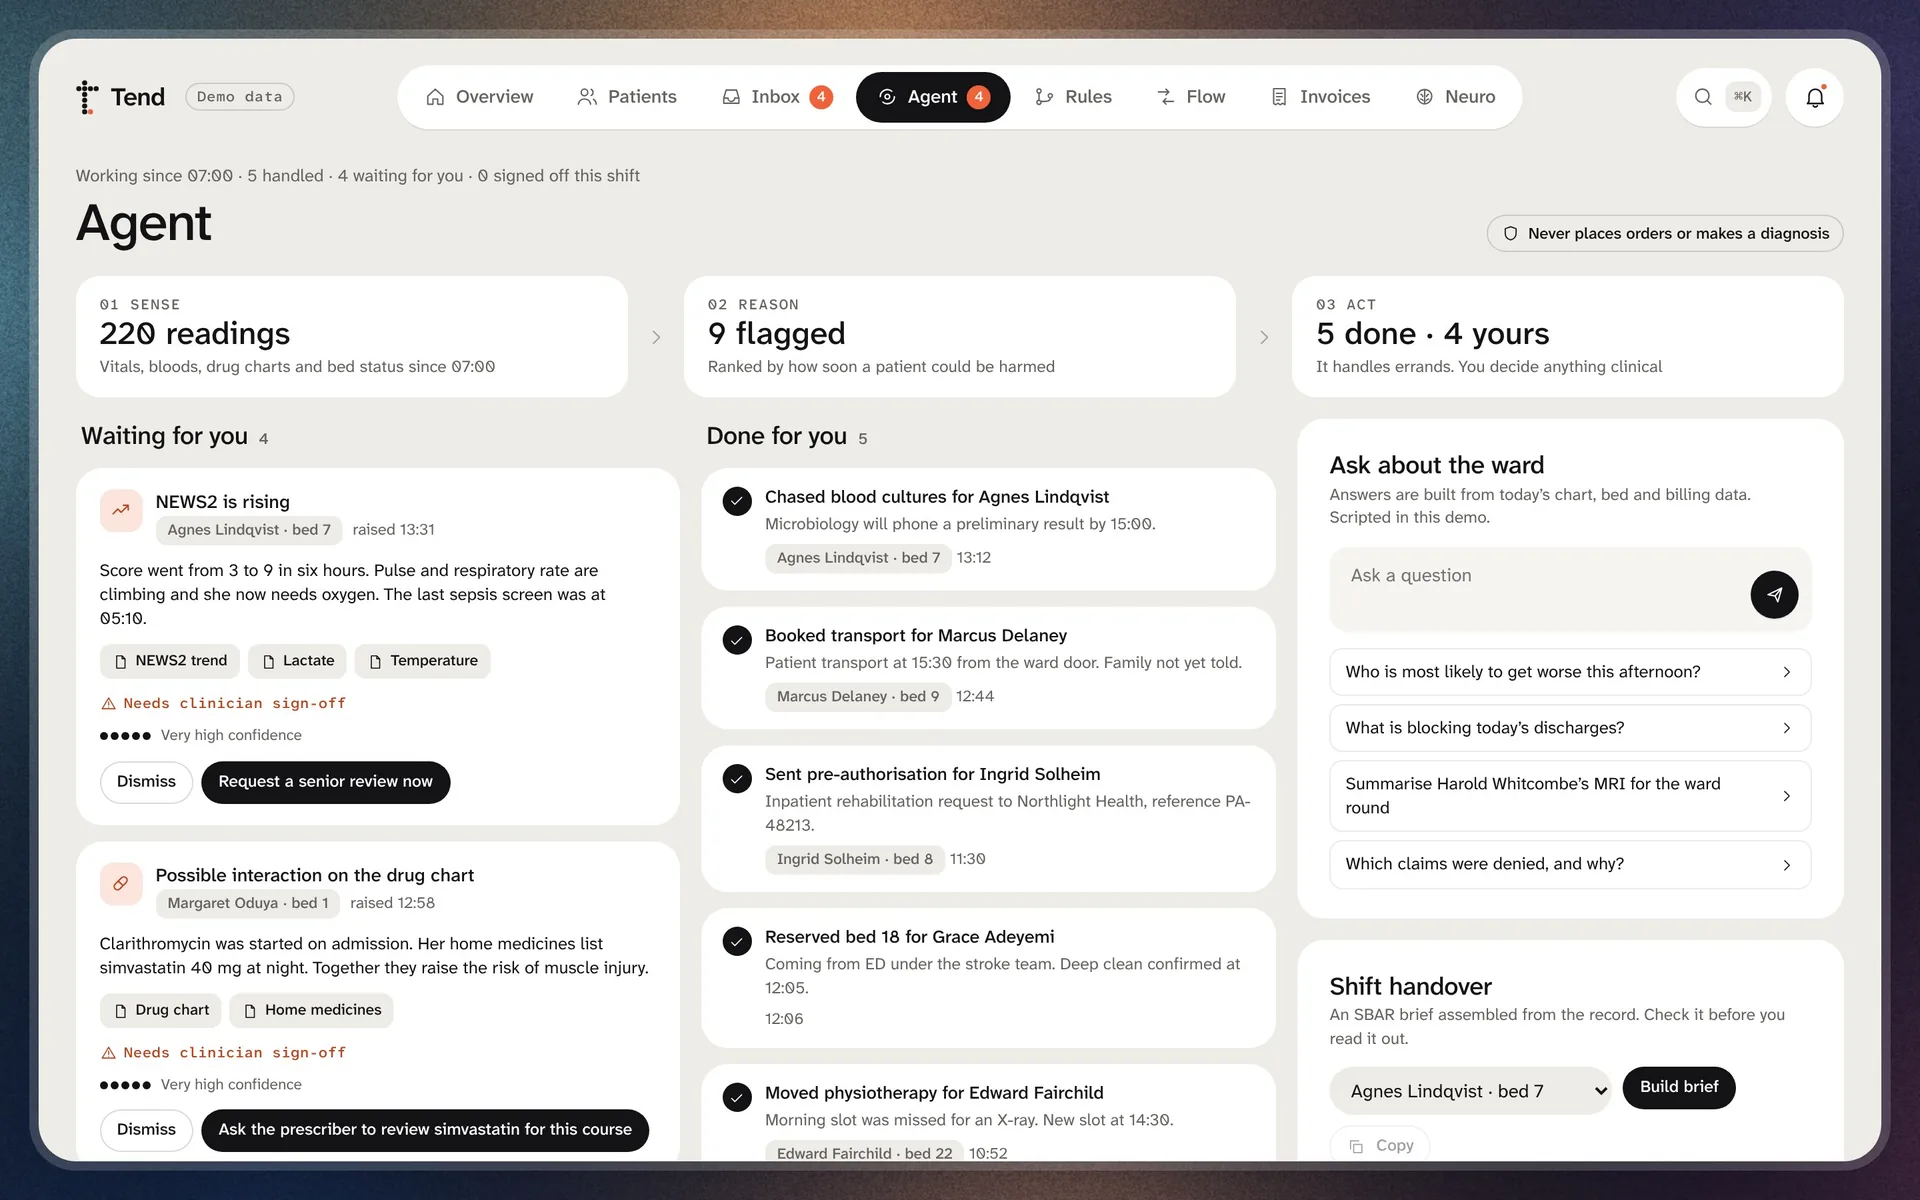
AI that acts silently is a safety risk. AI that gives advice with no reason gets ignored.
- Sense, Reason, Act. A strip that shows what it read, what it flagged, what it did.
- Waiting for you. Clinical items with evidence chips, a confidence level and a sign-off label.
- Done for you. Errands it handled, each logged with a time.
- Ask about the ward. Answers built from today’s data, with links into the chart.
- Shift handover. An SBAR brief you can check and copy.
Every suggestion shows its evidence. Clinical items always wait for a person. Errands are done and logged. Nothing is final, because everything has Undo. That is how trust is earned.
Try: Tap an evidence chip. Approve a card, then Undo. Ask one of the four questions.
Rules
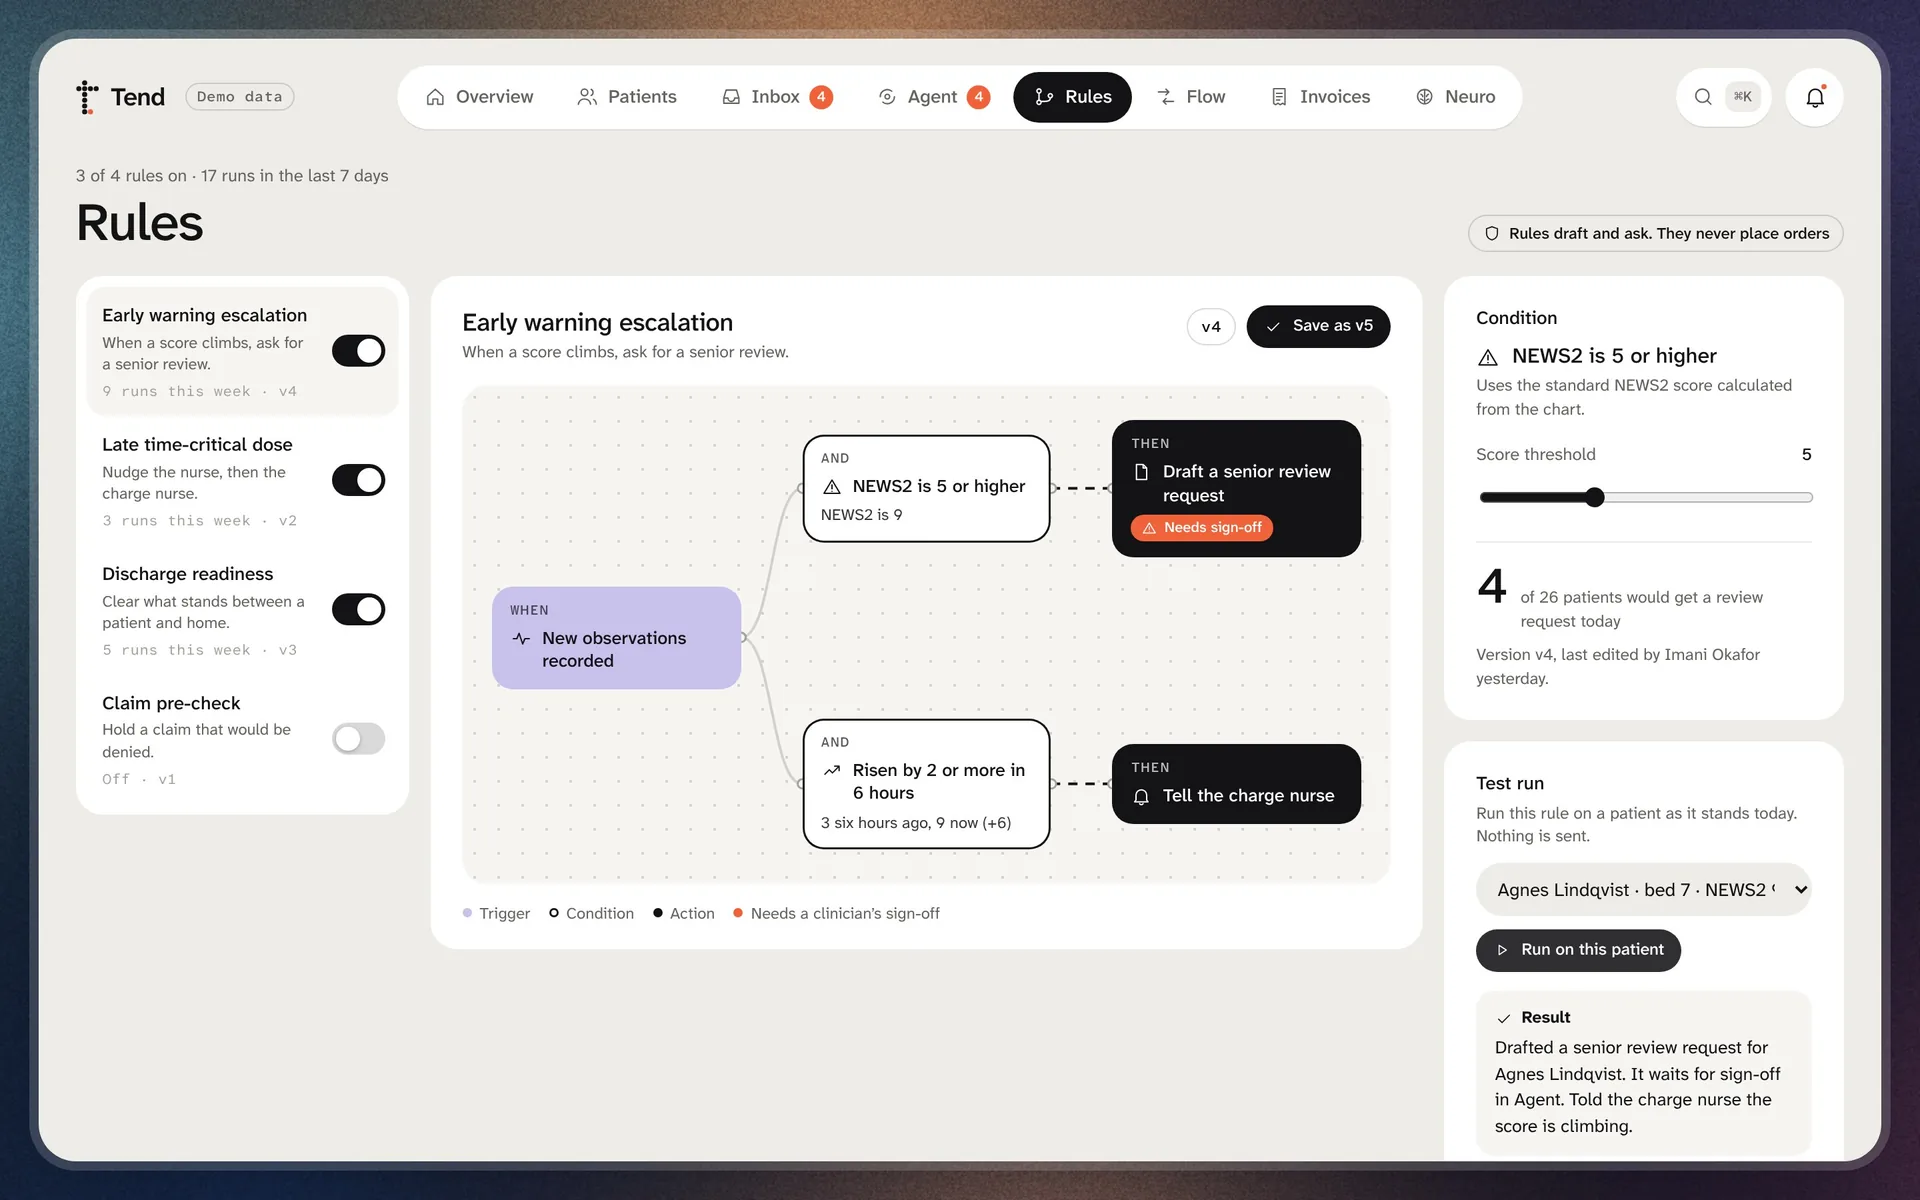
The logic of a ward, who to alert and when, sits in IT tickets or in people’s heads. Too many alerts cause alarm fatigue.
- A canvas. Trigger, conditions, actions, joined by wires.
- Sliders. Change a threshold and read how many of today’s patients it would have flagged.
- Test run. Pick a real patient. The path lights up, and the result is written out.
- Sign-off labels. Actions that need a clinician are marked, and cannot be turned off.
- Versions. Save as a new version with your name on it.
Clinical leads can tune an alert and see its cost before it ships. The test run makes a rule something you can watch, not something you take on trust.
Try: Drag the score threshold from 5 down to 3. Press Run on this patient. Try the other three rules.
Flow
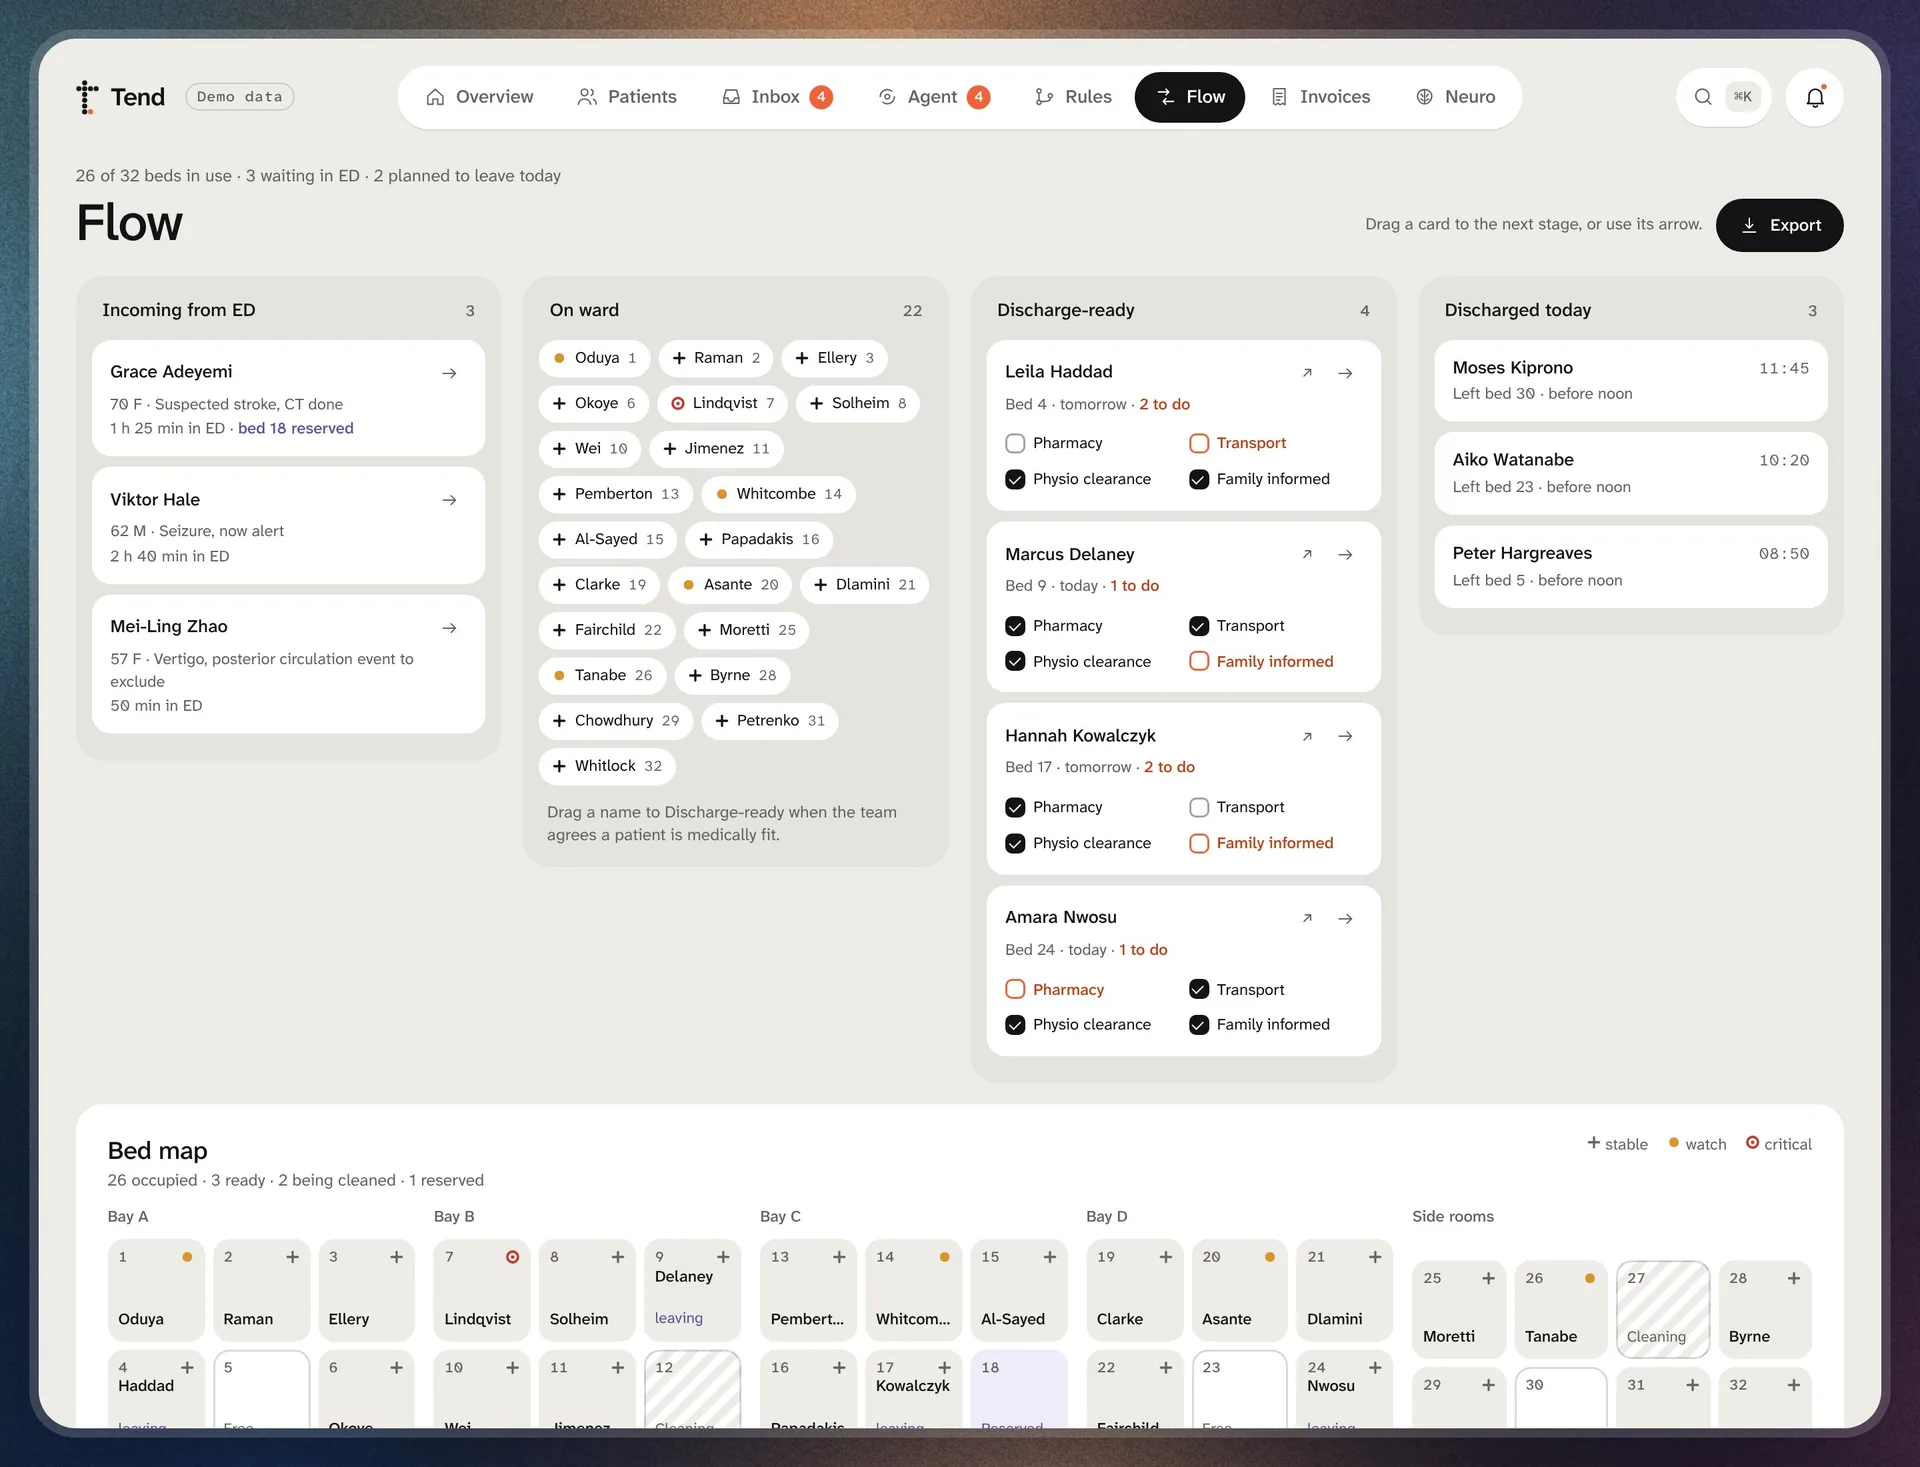
Discharges stall on one forgotten tick: pharmacy, transport or a call to the family. The bed stays blocked.
- Pipeline. Incoming from ED, on the ward, ready to leave, left today. Drag a card or use its arrow.
- Checklists. The blocker is marked in coral on the card.
- Bed map. Who is where, and which beds are clean.
- Billing link. Discharging a patient creates a draft claim.
The thing that stops a patient leaving is visible where the team looks. Moving a card changes the counts on the Overview, so the whole product stays in agreement.
Try: Admit a patient from ED. Try to discharge one with an open checklist.
Invoices
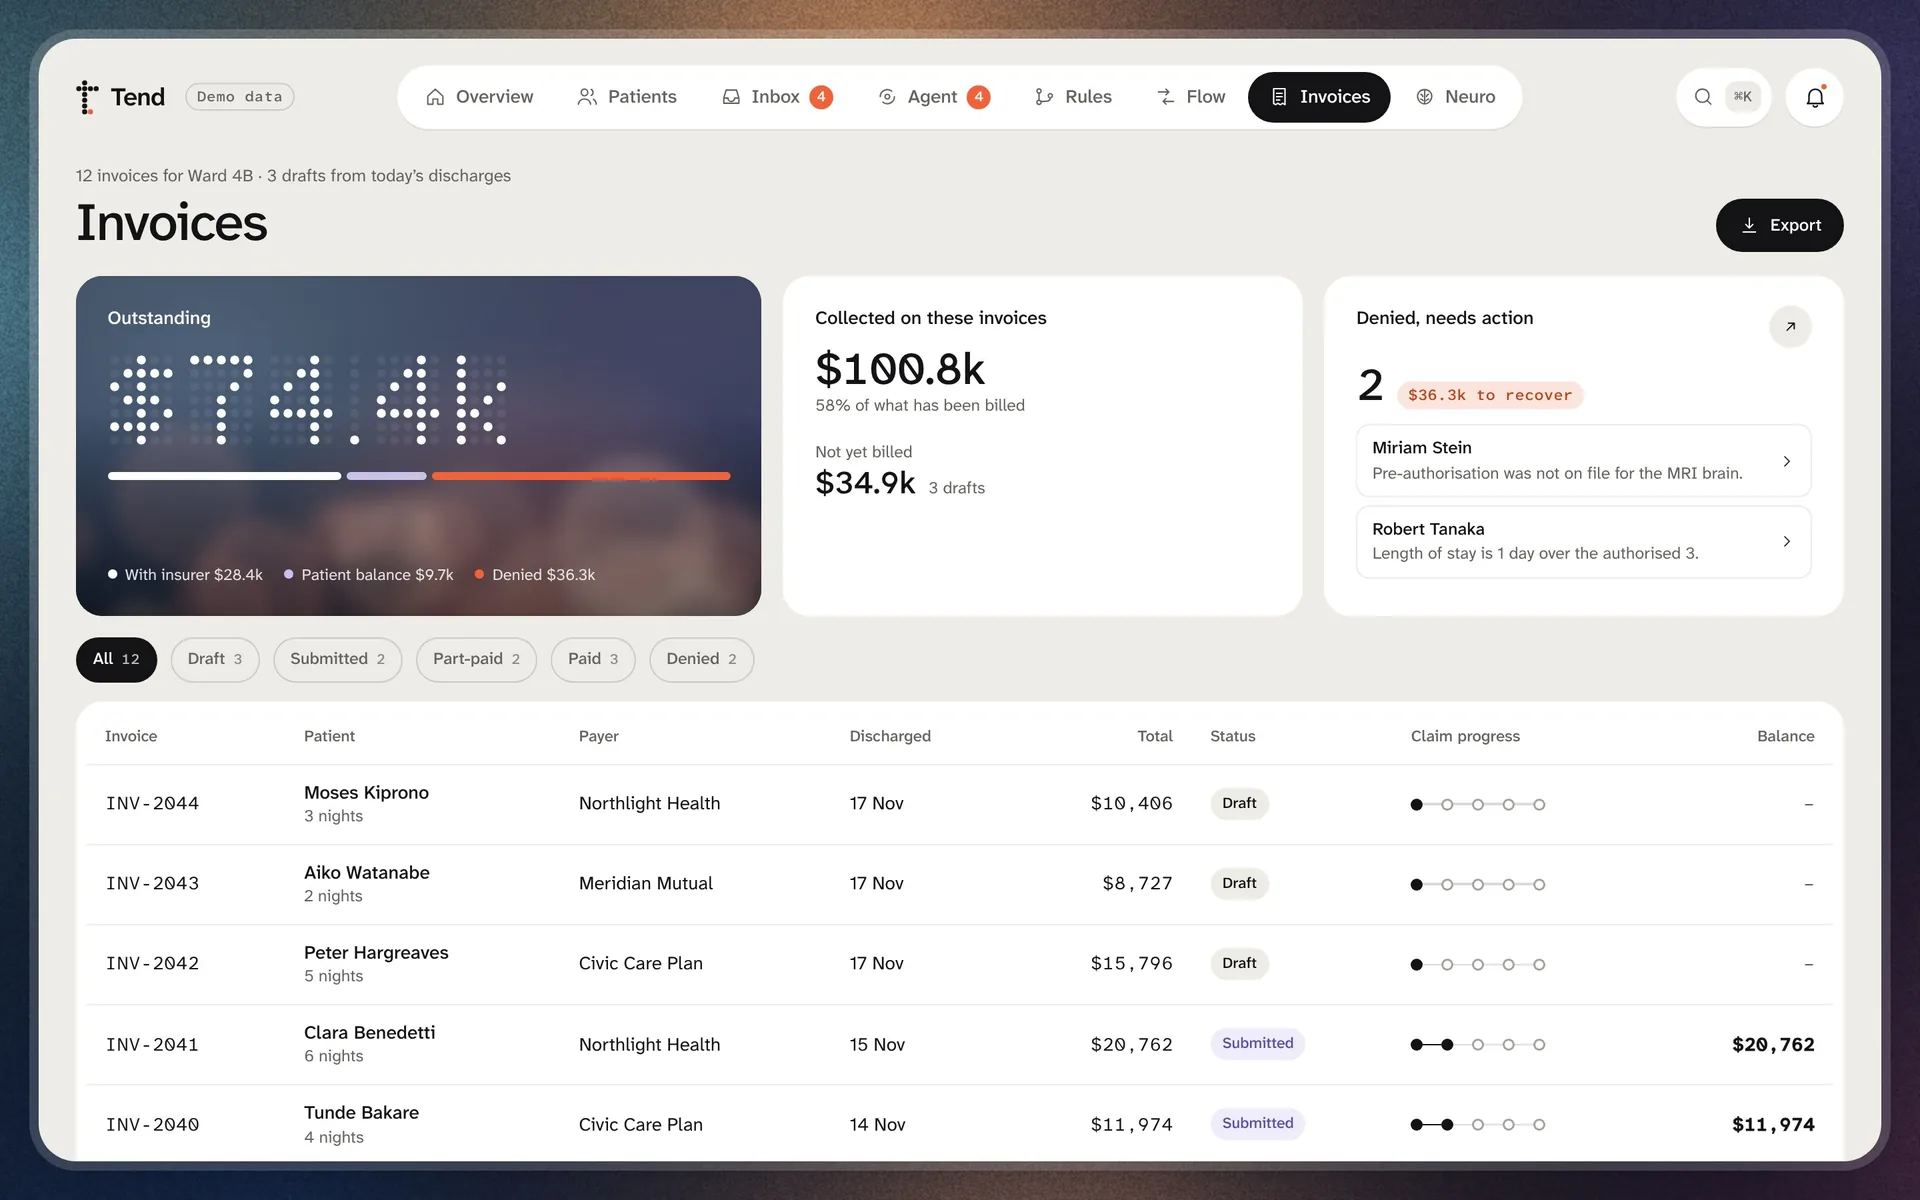
Billing is invisible to the ward. Claims are rejected weeks later for something that was fixable while the patient was still here.
- Outstanding. One number, split by who owes it.
- Claim progress. Draft, submitted, adjudicated, part-paid, paid.
- Denied queue. The reason, in words, with a resubmit button.
- Itemised drawer. A plain-language switch rewrites each line for the patient.
A claim denied for a missing pre-authorisation is fixed while the patient is still in. The plain-language switch means anyone on the ward can explain a bill without jargon.
Try: Open a denied claim. Turn on plain language.
Neuro
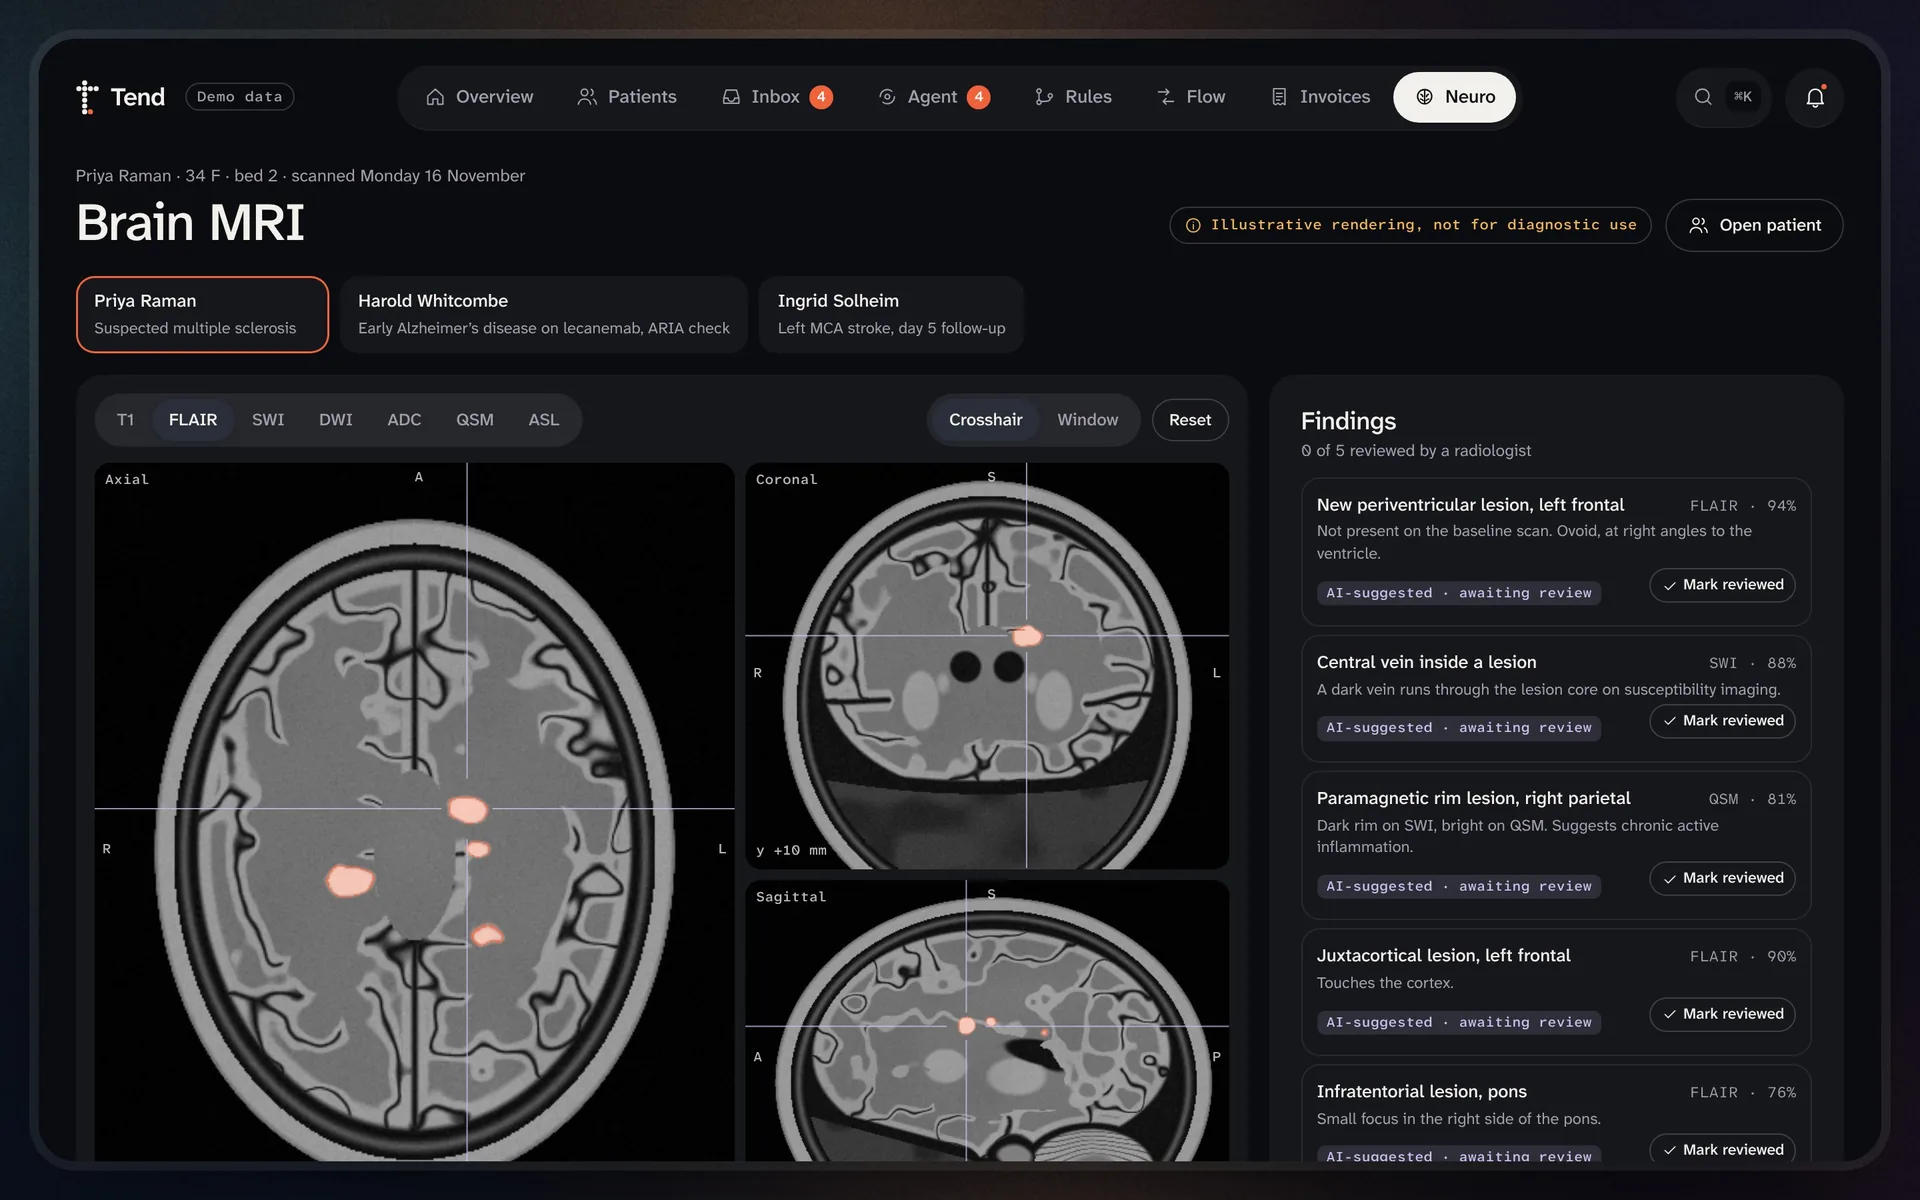
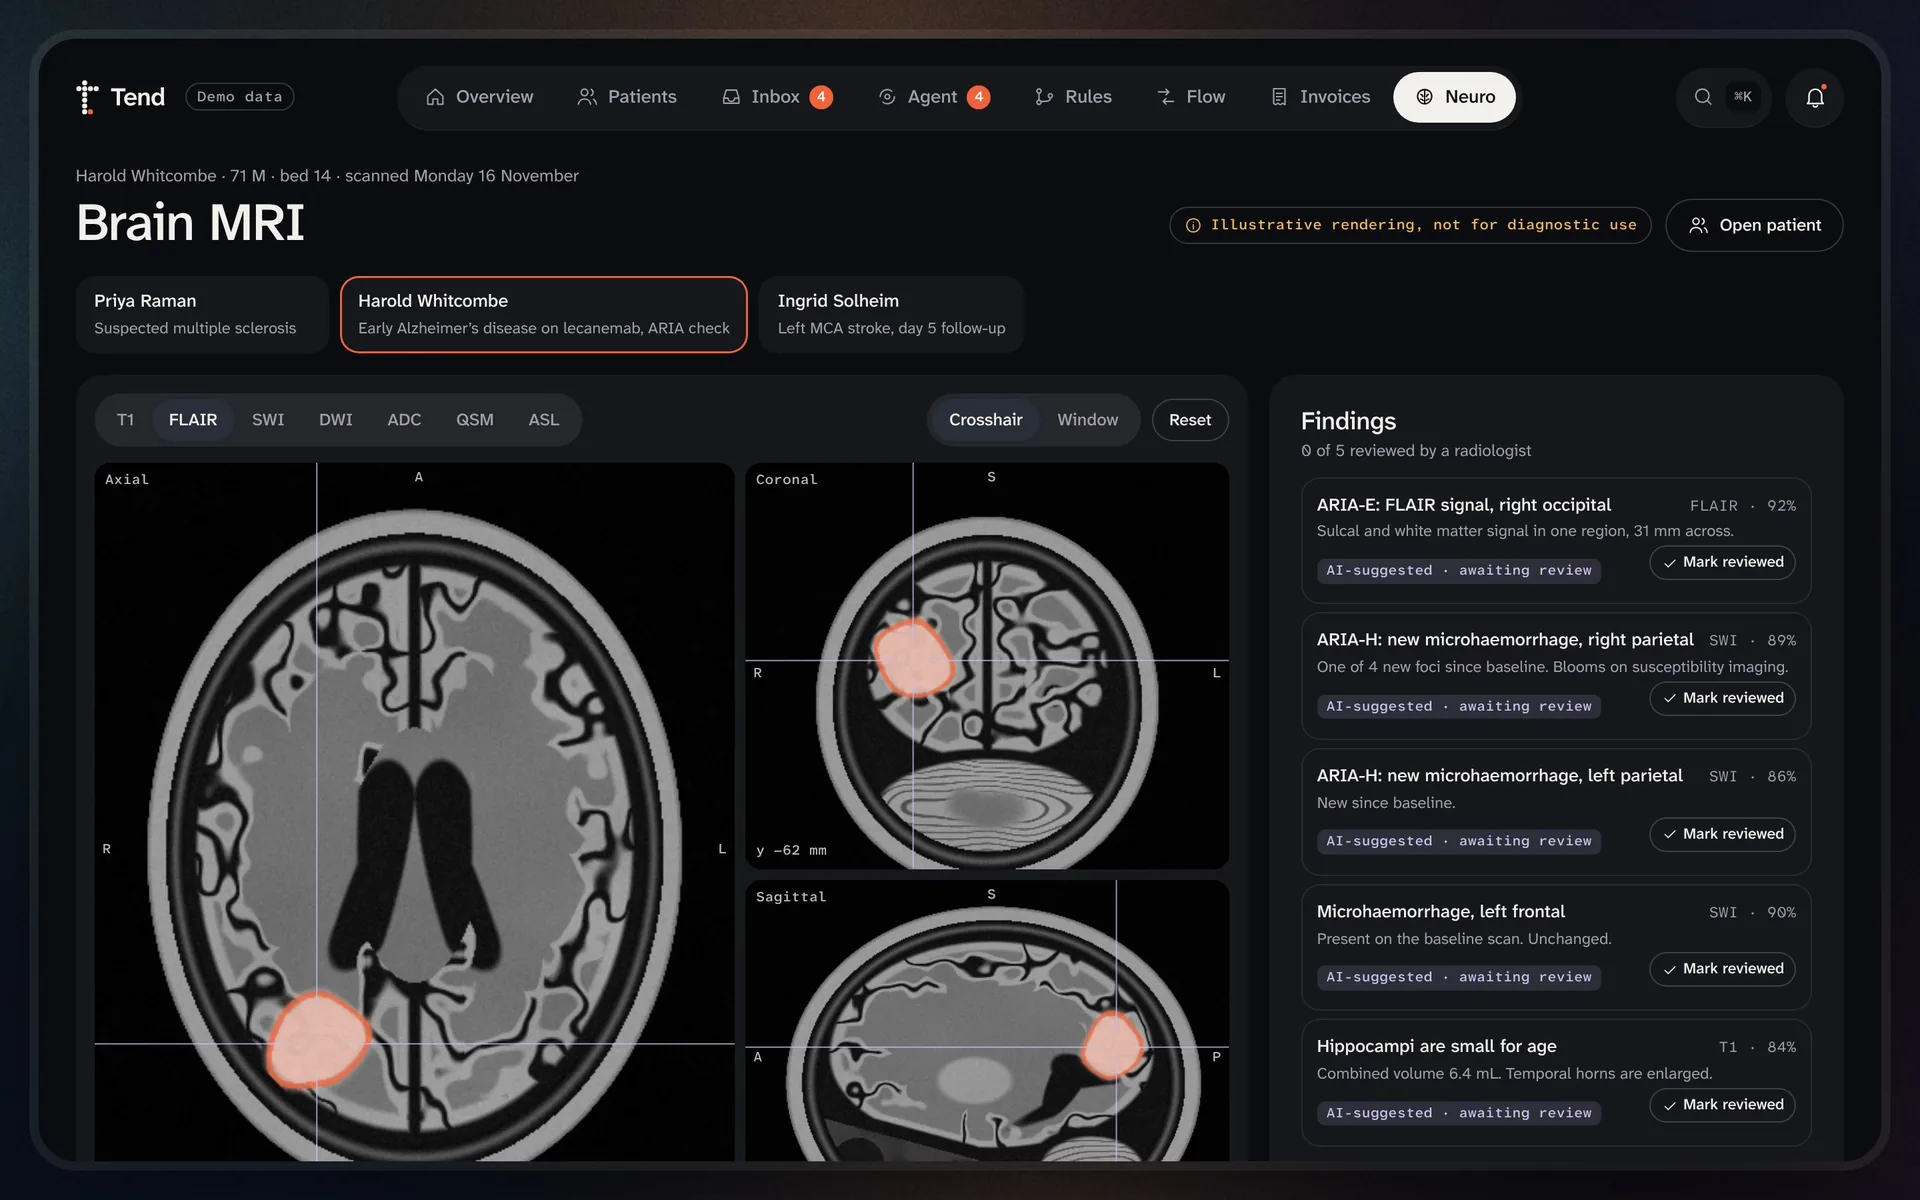
Brain MRI is read in a separate viewer, far from the chart. New MS and Alzheimer’s guidance asks for finer reading.
- Three linked planes with seven sequences, a crosshair and window controls.
- Findings list. Click one and the crosshair flies to it. Each is AI-suggested and awaits a radiologist.
- Centile chart, brain-age gap, tractography and a baseline wipe.
The scan lives beside the patient. Three cases show three jobs: an MS work-up, ARIA monitoring on lecanemab, and a stroke follow-up. Section 15 explains the research behind it.
Try: Switch case, scroll a plane, turn on the findings overlay.
A letter made of dots.
The idea. “Tend” means to look after. The dashboard draws every number as dots, so the logo is a lowercase t in the same four-by-six dot grid as the numerals.
The coral dot at the foot of the stem is the patient. It is the same coral the product uses for “now” and “attention”. The line of care ends on one person.
The name. Short, a verb, easy to say over a phone in a noisy ward.



Ten dots, no more. The grid is 4 columns by 6 rows. The crossbar sits one row down from the top and runs one dot left of the stem and two to the right, so it reads as a t and not as a cross. A symmetric cross would have looked like a medical cliché, or worse, like a dagger.
At 16 pixels the dots merge into a clean t. Below that, use the single coral dot.
Three voices, one job each.
Words in Atkinson Hyperlegible Next. IDs and doses in its Mono cut. Numbers that change in Tend Dot.
The Braille Institute made it so that letters are easy to tell apart for readers with low vision. That is exactly the job in a ward: a tired person reading a patient ID, a dose or a drug name at speed. It is free on Google Fonts under the SIL Open Font License. The Next release has seven weights, from ExtraLight to ExtraBold, and covers 150 languages.
It also looks less like an AI product. Most generated interfaces default to Inter or a geometric sans with a round “o”. This face has a slightly humanist, slightly quirky shape that feels designed for a purpose.
abcdefghijklmnopqrstuvwxyz
0123456789 £$%&/()@=?.-
Capital I, lowercase l and digit 1 have different shapes. Zero has a slash-like mark in the Mono cut.
In many sans fonts a capital I and a lowercase l are nearly the same stroke. Compare with how yours renders.
Fixed width keeps columns of times, doses and IDs aligned, so numbers can be compared at a glance.
Drawn on the logo's grid. Every glyph is a 5 by 7 field of round dots, the same dots as the mark, so a number on a ward screen always looks like Tend.
It is used only for counts, vitals and time, and only large. Anything a person must read quickly, like a name or a dose, stays in Atkinson, where look-alike letters are drawn apart.
| Candidates | What I liked | Why not |
|---|---|---|
| Atkinson Hyperlegible Next | Built for legibility. Seven weights. Matching Mono. Distinct letter shapes. Calm, human tone. | Wide at very large sizes. I set big display text in the light weights to balance it. |
| IBM Plex Sans | Sturdy and neutral. Good numerals. | Reads as technical, closer to a developer tool than a care setting. |
| Public Sans | Plain and accessible, made for public-sector sites. | Very neutral. Little character and no matching mono. |
| Source Sans 3 | Highly readable at small sizes. | Looks dated beside the rest of the system. |
| Inter | The safe UI default. | It is the AI-interface default, and capital I and lowercase l look the same. |
63 icons, one hand.
Every icon sits on a 24 pixel grid with a 1.5 pixel stroke, round caps and joins, and 3 pixels of padding. Shapes are made of circles, lines and simple curves, so they read at 16 pixels next to body text. They inherit the colour of the text, which means they work in the light and dark themes with no extra files.
- One idea per icon. No tiny details inside shapes.
- Open shapes where a line can end, so they feel light next to text.
- Medical icons are literal: a pill, a flask, a thermometer. Nothing decorative.
- Status uses its own three glyphs (plus, dot, ring), never an icon.
All 63 are exported as individual SVG files and as one sprite in the assets folder.
Quiet pictures for quiet moments.
Empty states are the moments when nothing is wrong: no alerts, no search results, an empty inbox. Stock photography would feel like marketing here, and a face on a “nothing to do” screen is odd in a clinical tool.
So the illustrations are drawn from the product’s own parts: dots, capsules and hairlines, in ink with one touch of coral or lavender. They sit in the interface, not above it.
Built for the desk, the bed, the pocket.
One system, five places it is used. Each screen is drawn at the exact shape of its device, then set into a photograph with correct perspective, so nothing is stretched or cropped.
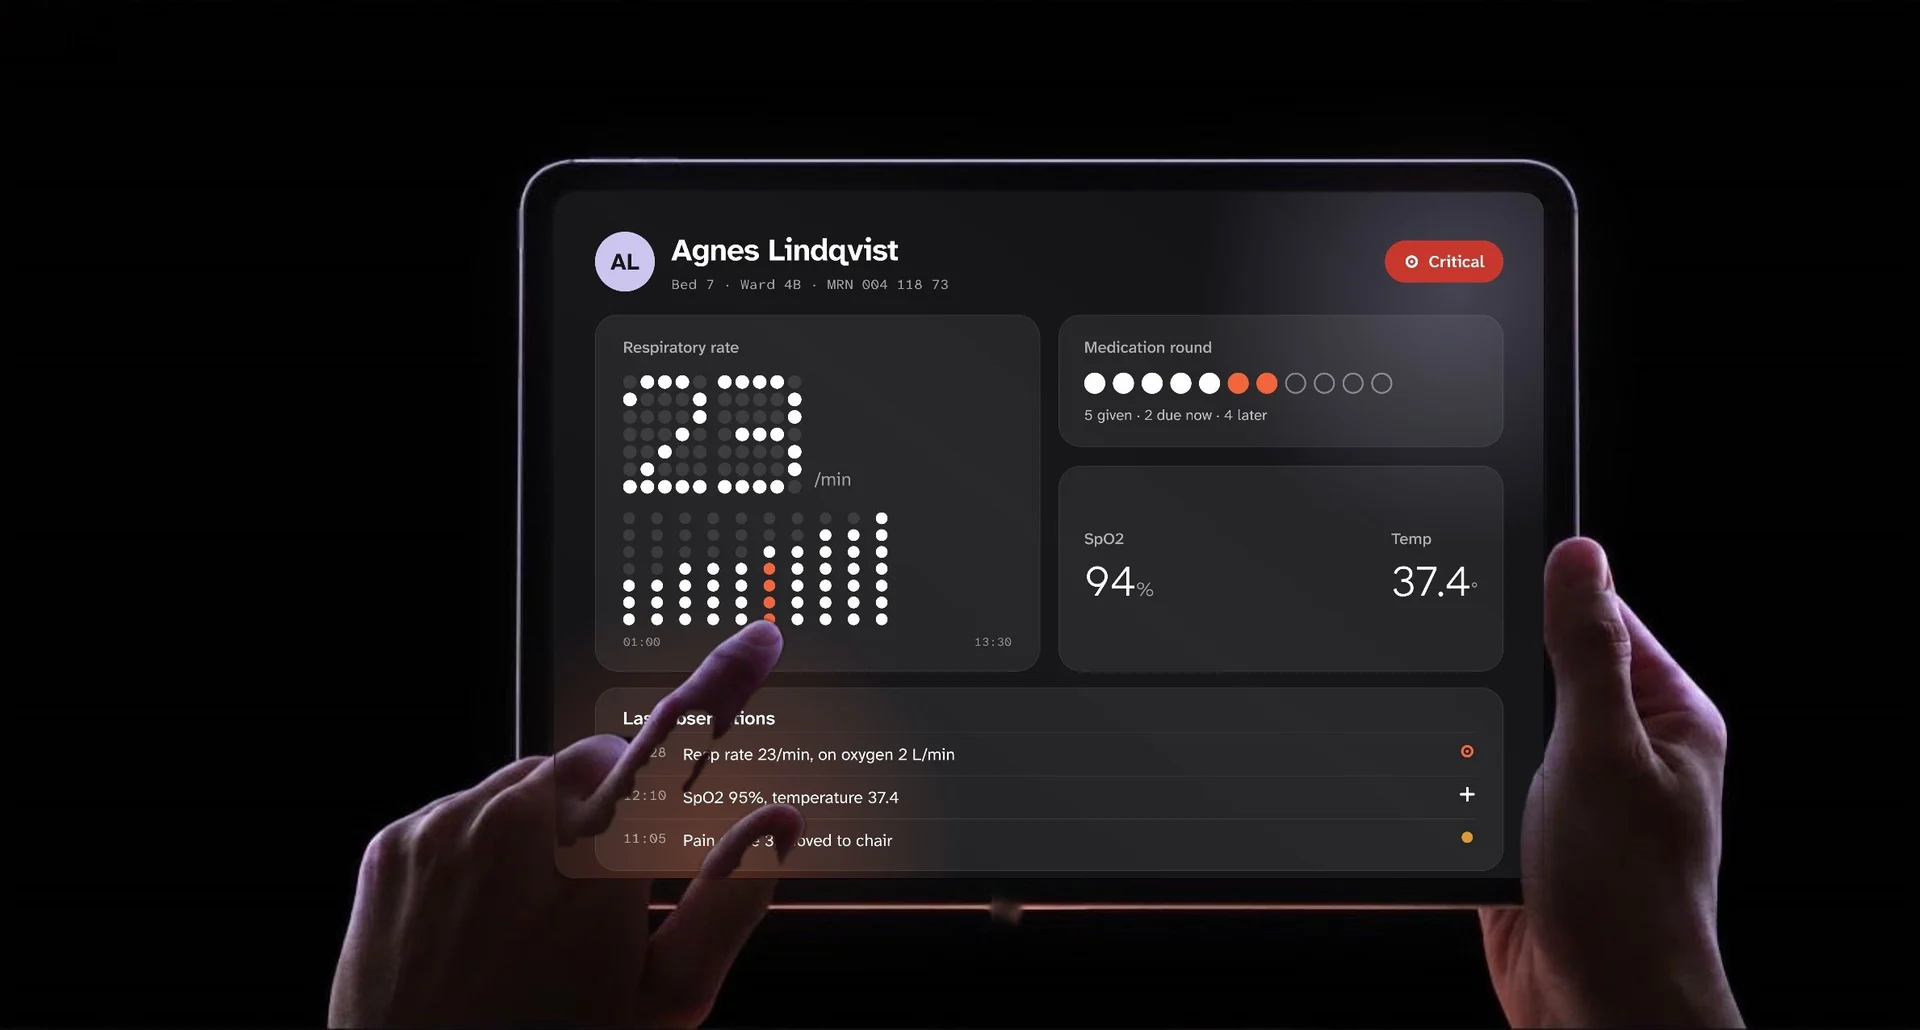 BEDSIDE TABLET
 WARD DISPLAY
 POCKET · HANDOVER, PULSE, PATIENT
 HANDHELD · PATIENT SCREEN
 CHARGE DESK
 ON THE WARD, AT DUSK
Photographed blank. Screens added after.
AI photographs fail the same way every time: warped bezels, extra fingers, a screen full of fake text.
So the picture and the interface are made separately. Each photograph is generated with a blank black screen, then the real Tend screen is drawn at that device's exact shape and warped onto it. Anything that passes in front of the glass, like a finger, stays in front.
 1 · GENERATED, SCREEN BLANK2 · TEND SCREEN ADDED
Generate blank
A reference image sets the camera, light and mood. The prompt asks for a flat, empty screen and no text anywhere.
Draw at native shape
The screen is designed at the device's own proportions, so a phone gets a real phone layout instead of a squeezed desktop.
Warp, mask, light
A perspective transform fits the corners. Fingers are masked in front. The screen throws a soft glow back onto the scene.
Movement is information.
Every animation answers a question: what changed, where did it go, what will happen. All of it stops under “reduce motion”, and the screen reads the same without it.
Capsule chart
Ink for the past, coral for today, lavender for the forecast. Switching the measure morphs the capsules, so you see the same beds become admissions.
A rule firing
In Rules, a test run lights the trigger, then each condition, then the actions that fire. Wires flow only along the path taken.
A live signal
A critical patient’s pulse tile breathes slowly. It is the only continuous animation in the product, so it means something.
Dot numerals
Counts such as beds occupied are drawn as dots that flicker into place, then settle. It gives numbers a physical feel without making them hard to read.
View transitions
Opening a patient from the list grows their row into the chart, so you never lose where you came from.
Every action reverses
Cards slide out when handled and a toast offers Undo. Speed without fear.
Built on recent neuroimaging.
The Neuro screen is the most ambitious in Tend. It is a working viewer of a procedural head model, not a real scan, and it is labelled as illustrative and not for diagnosis. Its features follow current practice:
- MS work-up. The 2024 revision of the McDonald criteria adds the central vein sign, paramagnetic rim lesions and the optic nerve as a fifth location. The viewer marks all three.
- ARIA monitoring. Anti-amyloid drugs such as lecanemab need MRI checks. FLAIR shows ARIA-E (swelling) and susceptibility imaging shows ARIA-H (microbleeds), so the viewer has both, plus a hold flag on the infusion.
- Normative charts. Brain measures are placed on lifespan centile charts, with a brain-age gap, so “small for age” is a number and not a feeling.
- 7T and deep-learning reconstruction. The acquisition card shows field strength and a reconstruction toggle.
- Human in the loop. Every AI-suggested finding stays “awaiting review” until a radiologist marks it.
What the research changed.
| Part | Version one | Version two |
|---|---|---|
| Navigation | 6 tabs | 8 tabs, adding Inbox and Rules new |
| Overview | Beds, discharges, medicines, demand, length of stay, ward field | Adds a workload heatmap with forecast cells, and an age view made of status shapes new |
| Agent | Cards with evidence and confidence | Adds the Sense, Reason, Act strip, so the agent’s method is visible new |
| Messaging | None | An inbox with chart context, drafted replies and a privacy flag new |
| Automation | None | A rule canvas with live “would have flagged” counts and test runs new |
| Brand | A placeholder ring | A dot-matrix t, colour and type system, icon set, illustrations new |
| Empty states | One line of text | Six drawn illustrations |
| Responsive | Desktop focused | Tested at desktop, tablet and phone widths, with screenshots in this study |
No results yet. Here is the test.
Tend is a concept with made-up patients, so I have no outcomes to report and will not invent any. Here is what I would measure in a pilot on one real ward, against that ward’s own baseline.
The core promise. Measured per escalation, before and after.
Published studies put documentation at roughly a quarter to 40 percent of a shift.
And the number of bed days lost to a missing tick on the checklist.
Too low suggests blind trust. Too high suggests the agent is noise. Both need watching.
- The Pharmaceutical Journal on the King’s Fund analysis: delayed discharge cost £2.7bn in 2025/26, £562 a bed day
- Healthcare Management: nearly 13,000 delayed discharges a day, close to one bed in ten
- Tandem Health: nurses’ documentation time, including the NYU Langone flowsheet study
- Medtronic summary of Schenk et al. (2017): documentation share of medical-surgical nursing time
- Pulse: nurse-led integrated monitoring and non-actionable alarms
- Montalban et al., Diagnosis of multiple sclerosis: 2024 revisions of the McDonald criteria
- Published appropriate-use recommendations for MRI monitoring of amyloid-related imaging abnormalities (ARIA) with anti-amyloid therapy
- Bethlehem et al., Brain charts for the human lifespan, Nature (2022)
- LBB: Applied Design and Braille Institute launch Atkinson Hyperlegible Next
- Adobe Fonts: Atkinson Hyperlegible Next, seven weights, 150 languages
- Reference case studies analysed: MediNexus, Vital (SpaTheory) and Keel
NEWS2 is the National Early Warning Score used across the NHS. Figures on delayed discharge are for England. Tend’s demo shows dollar amounts in billing, because the claims flow is modelled on a US-style payer system.